What is a medical appraisal?
A medical appraisal is an annual professional review of your work as a doctor. It is an opportunity to sit down with a trained medical appraiser, look back over the year you have had, reflect on your learning and clinical practice, and agree what you want to work on next.
I am a locum consultant in geriatric medicine and an independent medical appraiser. I undertake around five to ten appraisals a week, often with doctors in very different circumstances: established consultants, locums, international medical graduates and doctors having their first appraisal outside training. One thing that comes up repeatedly is that appraisal sounds more complicated than it really is.
The simplest way to think about it is as an annual professional check-in. It is not an examination, and a good appraisal should not feel like a test. It is a structured discussion about your whole medical practice, supported by evidence that you have continued to learn, reflected on your work and taken your professional responsibilities seriously.

Why does appraisal matter?
Keeping your medical appraisals up to date is one of the simplest ways to make revalidation less stressful. Each annual appraisal helps build a clear record of your work, learning and reflection, so that when your revalidation date approaches you are not trying to reconstruct several years of evidence. It also helps your responsible officer or suitable person make an informed recommendation, where you have one.
Medical appraisal is part of the system that supports GMC revalidation. Most licensed doctors outside formal postgraduate training are expected to participate in an annual whole-practice appraisal every 12 months. Revalidation usually takes place every five years, and your appraisal record is one of the main ways of demonstrating that you are keeping your knowledge, skills and practice up to date.
There is also a more immediate benefit. Appraisal gives you time to look at a year of work that may otherwise have passed in a blur. You can discuss achievements, challenging cases, complaints or significant events, changes in your job, what you have learned and what you want to improve. Ideally, you should leave the meeting with a realistic personal development plan rather than simply a signed document.
A gap in your appraisal history does not automatically mean you cannot revalidate. There can be legitimate reasons for missing an appraisal, and the circumstances can be considered. But repeated or unexplained gaps can mean additional questions, more required evidence and sometimes a deferral. Keeping up to date is generally easier than trying to reconstruct several years of work later.
What does an appraisal actually review?
The discussion is based on Good medical practice and looks at your whole scope of medical work—not only your main job. That might include NHS employment, private practice, locum shifts, teaching, research, management or other roles for which you use your medical registration.
Most appraisal portfolios ask you to cover several areas:
Scope of work: where you have worked, in what roles and what responsibilities you have undertaken.
Continuing professional development (CPD): your learning over the year, what you took from it and how it has informed your practice.
Quality improvement: how you have reviewed the quality of your work and identified or made improvements.
Significant events, complaints and compliments: relevant matters you have been involved in, including reflection and learning where appropriate.
Feedback: patient and colleague feedback, where relevant, together with other feedback about your work.
Reflection and professional development: successes, difficulties, changing circumstances and priorities for next year.
You do not need to have something dramatic to say under every heading. Many doctors have no significant events or complaints to declare during a particular appraisal year. The important thing is to provide an accurate account of your practice and engage meaningfully with the areas that apply to you.
Appraisal outside training is different from ARCP
If you have recently finished foundation training, the difference can be surprising. During foundation or specialty training, much of your attention is on the curriculum, workplace-based assessments and ARCP. You need to demonstrate progression: that you have developed new competencies and are ready to move to the next stage of training.
Outside a formal training programme, appraisal has a different emphasis. The focus is on maintaining your professional standards, keeping your skills and knowledge current, reflecting on your work and identifying sensible improvements. It is not a requirement to prove that you have progressed to a new clinical grade every year.
That does not mean the process is meaningless or that learning stops. It simply means you are no longer being assessed against a training curriculum in quite the same way. Doctors in GMC-approved training ordinarily meet their revalidation requirements through the training framework, including ARCP, rather than through a separate standard annual appraisal.
Quick comparison: ARCP and annual appraisal are related to professional oversight, but they are not the same process and they serve different purposes.
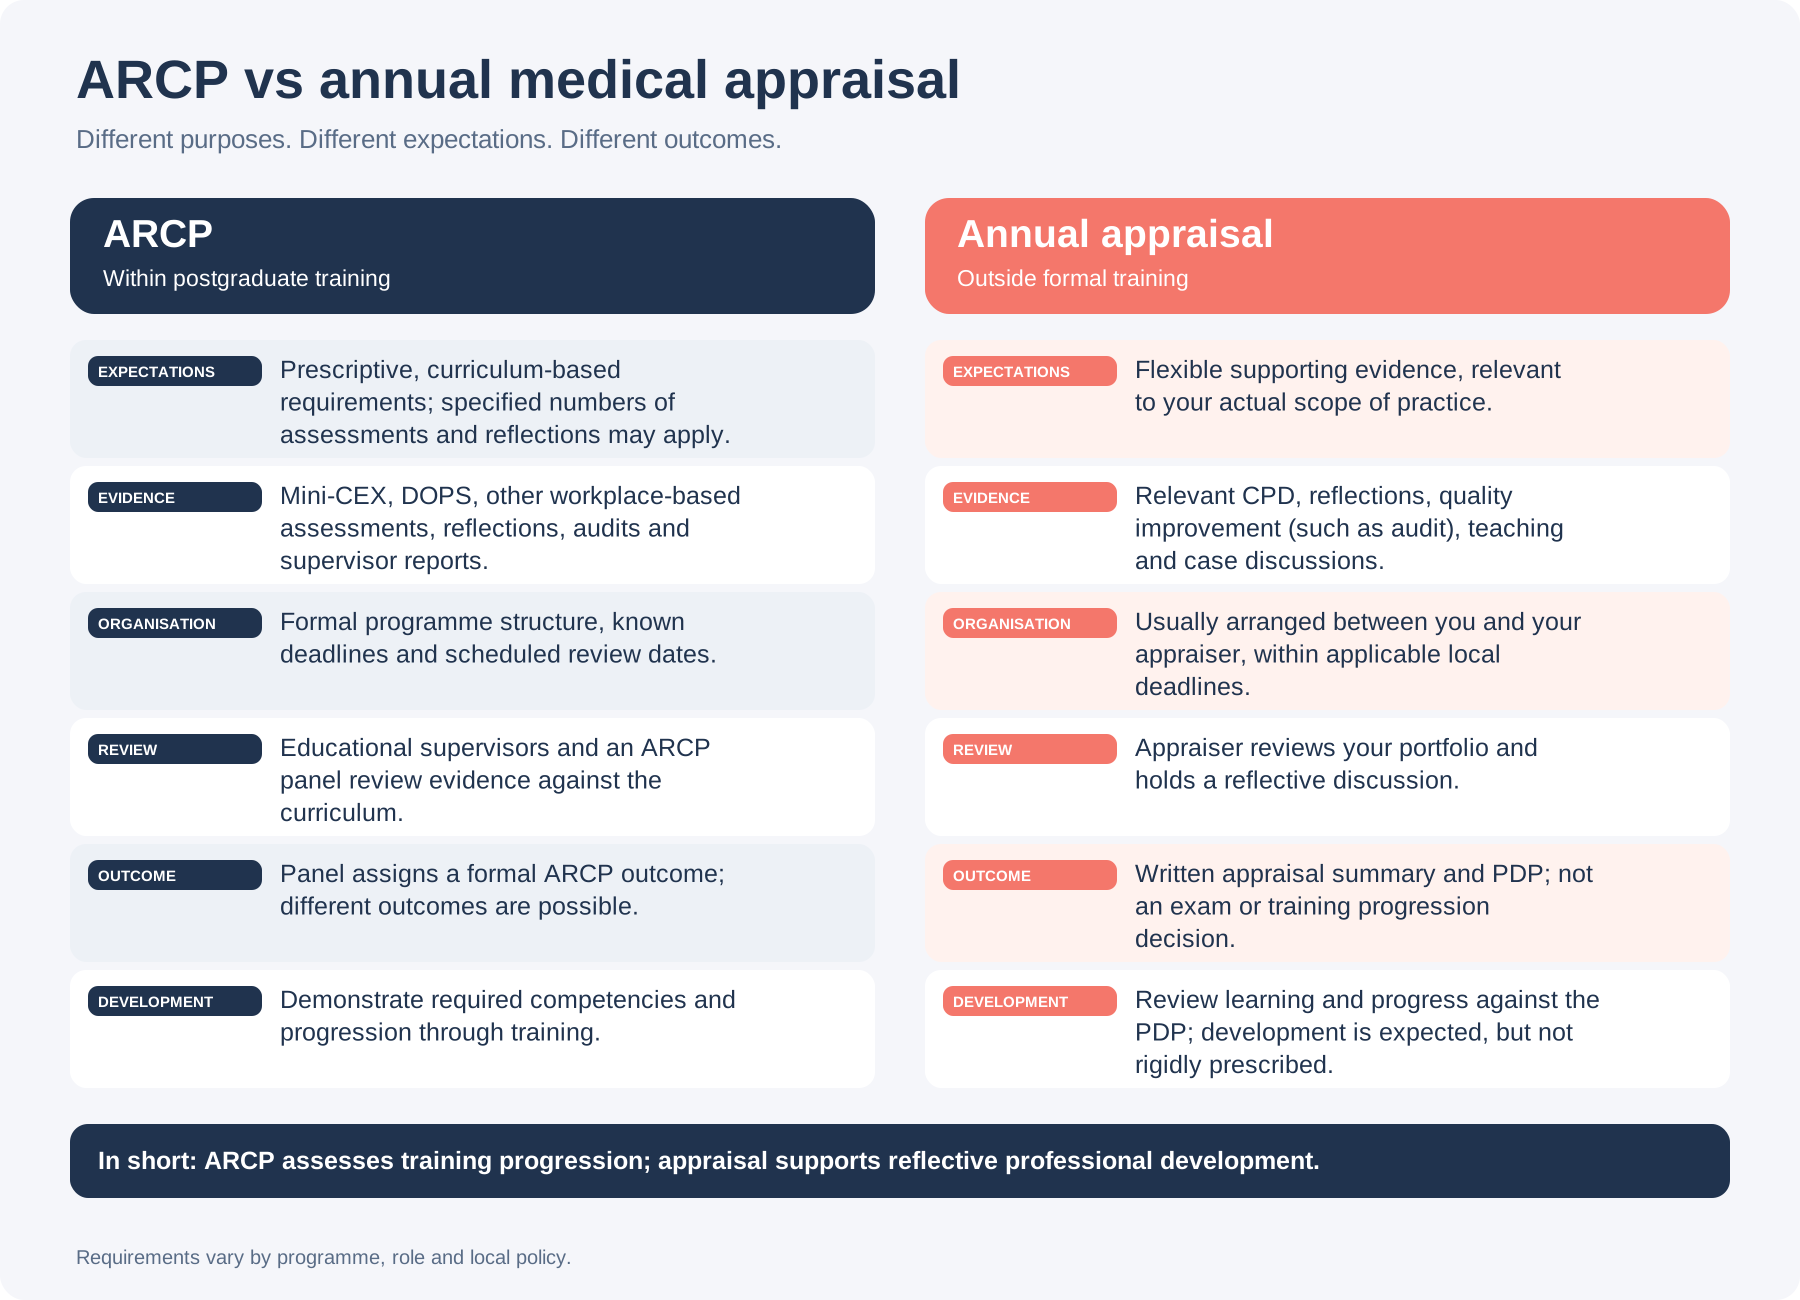
Figure: ARCP applies to doctors in GMC-approved training programmes, whereas annual medical appraisal is the usual process for licensed doctors outside formal training.
What happens in practice? From portfolio to signed report
Although different employers and software platforms use different forms, the overall process is usually straightforward.
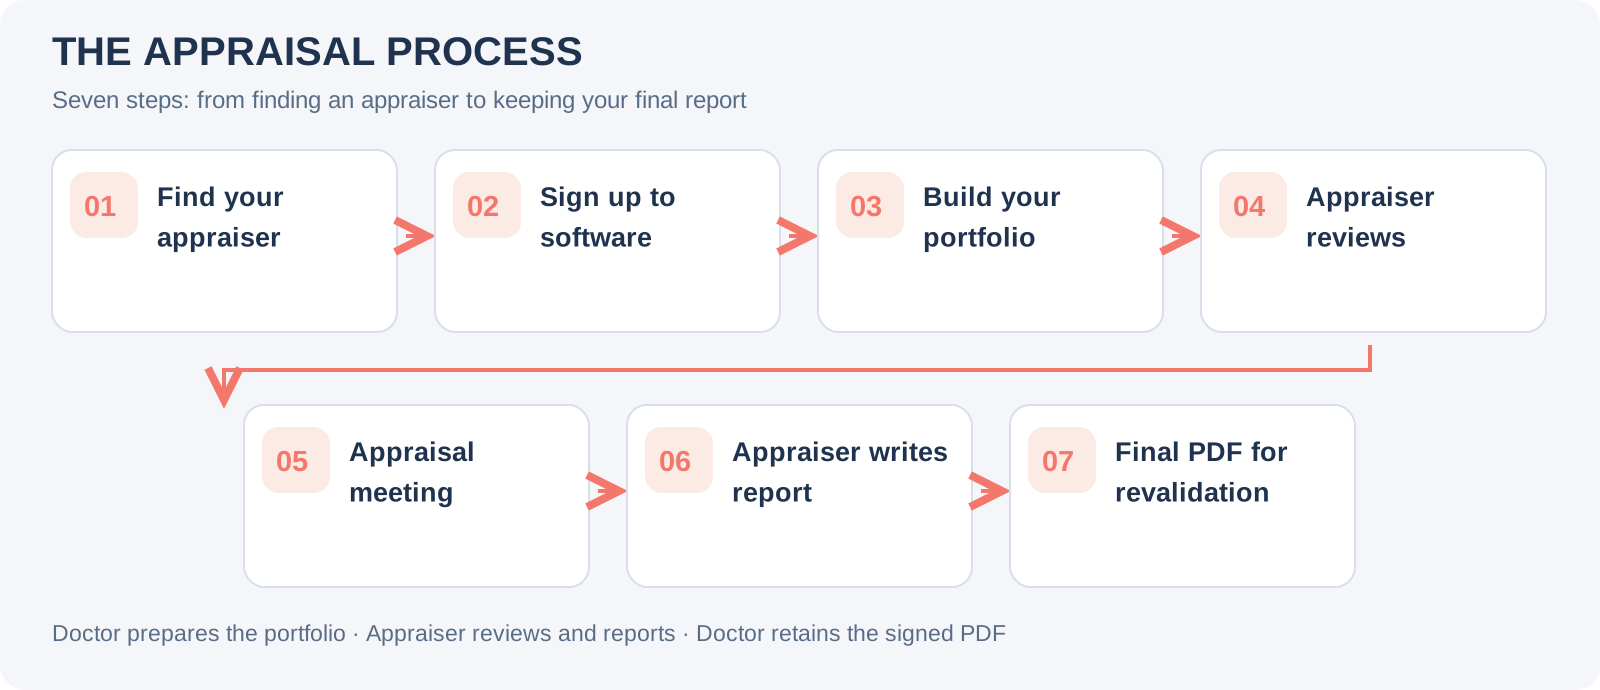
1. Identify and arrange your appraiser
Find out who will carry out your appraisal. Your employer or designated body may arrange this, or you may need to find an appraiser independently. Confirm the arrangements and agree a date.
2. Sign up to appraisal software
Register with the agreed platform, such as Improval, and create your appraisal portfolio.
3. Organise your evidence in the portfolio
Complete your scope of work, learning and CPD, quality improvement, feedback, reflections and declarations. Gather evidence throughout the year rather than doing everything at the last minute.
4. Have your appraiser review the portfolio
Share the completed portfolio in good time. Your appraiser reviews the information in advance and may ask you to clarify or add supporting details.
5. Attend the appraisal meeting
Meet your appraiser online or face to face. Discuss your work, learning, challenges and professional development, and agree objectives for your personal development plan (PDP).
6. Your appraiser completes the report
Following the meeting, the appraiser prepares the appraisal report, including a summary of the discussion and agreed PDP. Review and sign off the report through the agreed process.
7. Save your final signed PDF for revalidation
Once the report is signed off, download the final PDF and retain it securely. It forms part of your appraisal record and provides evidence of your ongoing engagement with appraisal at revalidation.
What does a well-prepared appraisal look like?
From an appraiser’s perspective, the strongest portfolios are not necessarily the largest. They give a clear picture of what the doctor actually does and how they have continued developing over the year.
A complete and credible description of every relevant part of the doctor’s work.
Learning collected throughout the year, with useful reflection rather than just certificates.
Relevant mandatory training up to date for the doctor’s work.
Appropriate quality improvement activity, with a clear explanation of what was reviewed or learned.
Honest discussion of achievements, challenges, complaints or events where applicable.
A sensible PDP that the doctor can realistically act on over the next year.
For example, if you regularly attend grand rounds, MDT meetings or teaching sessions, do not just say that you attended them. Keep a short record of what you learned. If a case changed how you approach a clinical problem, document the learning in an anonymised reflection. This makes the portfolio more meaningful and far easier to prepare.
Common mistakes—and how to avoid them
Leaving everything until the last minute
This is probably the easiest problem to prevent. Trying to reconstruct a year of CPD, cases and reflections the night before appraisal is unnecessarily stressful. Keep a running record throughout the year, even if it is only a few lines at a time.
Including only your main job
Appraisal is intended to cover your whole scope of medical practice. If you locum in multiple hospitals, undertake private work, teach or do another medical role, do not leave significant work out simply because it was not your substantive post.
Mistaking certificates for reflection
Certificates can evidence attendance, but they do not always explain what you learned or how it affected your work. A brief, genuine reflection is often more useful than uploading dozens of similar certificates without context.
Confusing appraisal with revalidation
An appraisal is normally annual. Revalidation is the GMC’s periodic decision, usually every five years, about whether you can continue to hold a licence to practise. A completed appraisal contributes to revalidation; it is not the revalidation decision itself.
Assuming someone else will arrange it
Doctors in training or permanent employment are often prompted by an established system. Locums, portfolio-career doctors and some IMGs may not receive the same reminders. Check your own arrangements rather than discovering a gap when revalidation approaches.
How appraisal connects to revalidation
Think of appraisal as building a record over time. Each year adds evidence about your professional work, development and reflection. At revalidation, the GMC considers the recommendation from your responsible officer or suitable person where applicable, together with other relevant information. Doctors without one follow a different GMC process.
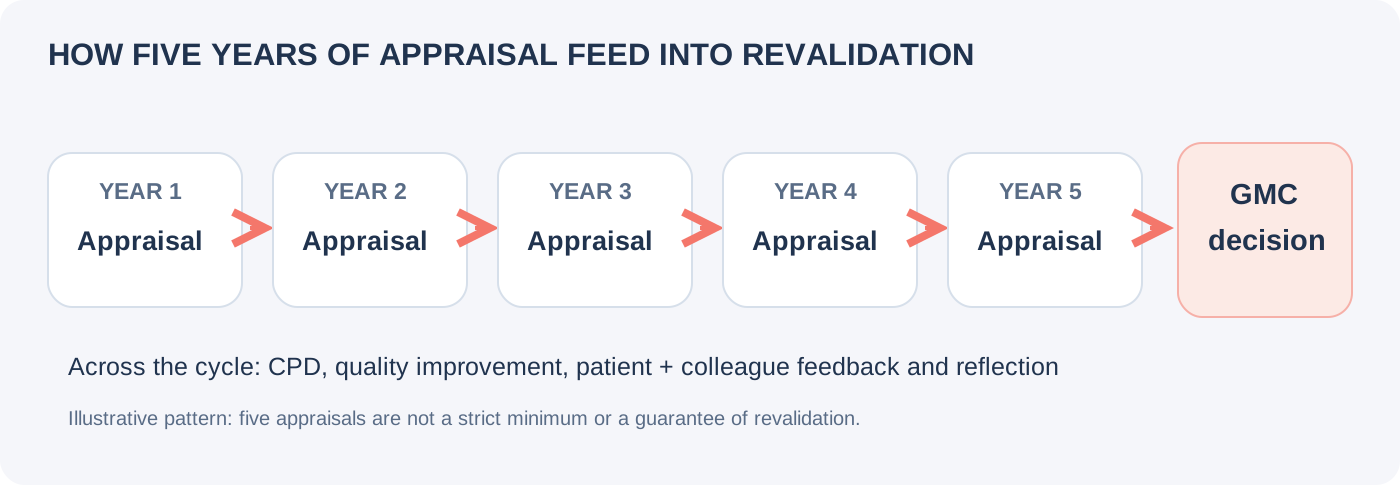
Patient and colleague feedback and quality improvement activity are also important parts of the revalidation picture. They should be planned across the cycle rather than treated as tasks to complete in the final few weeks. There is no universal rule that exactly five completed appraisals guarantee revalidation, or that fewer than five automatically prevent it.
There is another reason to keep your revalidation arrangements organised. Doctors who have a responsible officer or approved suitable person normally follow the recommendation-based route, supported by their appraisal record. Doctors without either follow a different GMC pathway, which may include a formal revalidation assessment. Keeping up with appraisal and establishing the appropriate revalidation connection early can help you avoid unnecessary complications, but an appraisal alone does not remove an assessment requirement.

Do you still need appraisal if you are between jobs?
This is a particularly common question for F3 doctors, locums and international medical graduates. If you retain a GMC licence, you remain responsible for engaging with the relevant revalidation arrangements, even when your clinical work is limited. Whether an appraisal is meaningful, what supporting information is appropriate and whether retaining a licence is sensible all depend on the circumstances.
If you are out of work or working overseas for an extended period, seek advice early rather than simply leaving your appraisal record blank. Our separate guide, “Do I Need a Medical Appraisal?”, looks at these situations in more detail.
The bottom line
Appraisal is not simply a paperwork exercise or a box to tick for the GMC. Done well, it is a useful annual conversation about what you have been doing, what you have learned and what you want to improve.
The practical formula is simple: know who is organising your appraisal, record your work and learning as you go, be open during the meeting and keep the final documentation. If you do those things each year, revalidation is usually much easier to manage.
Sources and review
- Last reviewed
- 22 October 2026